
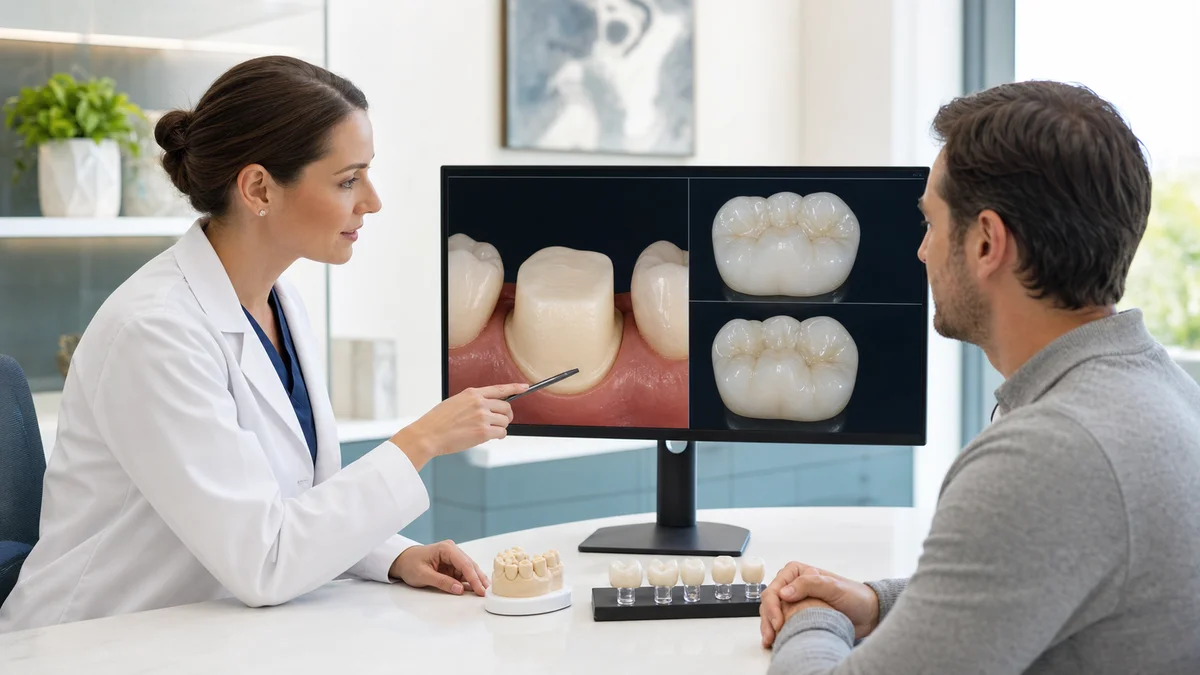
Quick answer: zirconia crowns risks include loss of retention, chipping or fracture, rough-surface wear on an opposing tooth, shade or translucency mismatch, gum irritation from poor contours, decay at an imperfect or poorly maintained margin, and difficulty removing the crown. Risk depends on diagnosis, zirconia type, tooth preparation, laboratory design, polishing, bonding, bite, and long-term care.
Online discussions of zirconia crowns risks often treat every zirconia restoration as the same. In reality, “zirconia” describes a family of dental ceramics with different formulations, translucency, strength, and indications. A full-contour monolithic crown is not identical to a zirconia framework covered with veneering porcelain. A crown on a natural tooth also faces different biological considerations from one attached to an implant.
Zirconia can be a useful restorative material, but no crown is risk-free or permanent. Outcome depends on why the tooth needs coverage, how much sound structure remains, whether disease is controlled, how the tooth is prepared, the material selected, the accuracy of scanning and laboratory work, surface finishing, cementation, bite, and maintenance. Zirconia crowns risks should therefore be discussed as a treatment-system question, not as proof that the ceramic itself is inherently dangerous.
This guide explains realistic concerns without offering a remote diagnosis or guaranteed result. It can support a conversation about alternatives, consent, and maintenance. For a broader view of restorative care, see Redent Klinik’s English patient resources, then ask your dentist how the material choice relates to your specific tooth.
1. What are zirconia crowns, and why are they used?
A dental crown is a restoration that covers a prepared tooth to restore shape, appearance, strength, or function. The American Dental Association’s MouthHealthy resource notes that crowns can reinforce teeth with large fillings, protect weak or broken teeth, attach bridges, and cover dental implants. Crown treatment on a natural tooth requires removal of some tooth structure, so the need and alternatives should be established first.
Zirconia is an oxide ceramic used in CAD/CAM workflows. A laboratory or in-office system designs a restoration from a scan, mills it from a pre-sintered blank, and sinters it to develop its final properties. The FDA’s device documentation for contemporary zirconia materials describes their use for crowns and bridges and assessment under standards for dental ceramics and biocompatibility. This does not mean every formulation is interchangeable or suitable for every design.
When considering zirconia crowns risks, distinguish between:
- Monolithic zirconia: the crown is primarily one full-contour zirconia structure, with external staining or glazing as needed;
- Layered zirconia: a zirconia framework supports a veneering ceramic intended to improve appearance;
- Higher-strength, lower-translucency formulations: often considered where forces or framework demands are greater;
- Higher-translucency formulations: designed for improved optical properties but with different mechanical characteristics;
- Tooth-supported crowns: cemented or bonded over a prepared natural tooth;
- Implant-supported crowns: connected to an implant restoration, with different retention and tissue considerations.
When weighing zirconia crowns risks, a material label should be followed by its formulation, design, location, thickness, and manufacturer instructions. “The strongest zirconia” is not automatically the most aesthetic, while “the most translucent” is not automatically right for a high-load bridge.
2. Zirconia crowns risks begin with the decision to crown the tooth
Before focusing on ceramic choice, the dentist determines whether a full crown is necessary. Leeds Teaching Hospitals explains that crowns rebuild teeth weakened by decay, large restorations, wear, or root canal treatment, but that some designs require more tooth removal than others. In selected cases, a direct filling, bonded onlay, veneer, or no immediate treatment may preserve more structure.
For a natural tooth, zirconia crowns risks include risks shared by all full-coverage crowns: removal of sound tissue, temporary sensitivity, irritation of the pulp, and the possibility that the tooth later needs root canal treatment. These outcomes are not caused by zirconia alone. They relate to the tooth’s starting condition, preparation depth, heat and trauma control, remaining dentine, sealing, and biological response.
In evaluating zirconia crowns risks, active decay, extensive gum disease, poor plaque control, and uncontrolled grinding should be addressed in planning. A crown does not cure gum disease or make a tooth immune to decay. If the underlying tooth is cracked deeply, has insufficient support, or has a poor periodontal prognosis, covering it without addressing that condition can lead to failure regardless of material.
3. Chipping and fracture: monolithic versus layered designs
Chipping and fracture are among the most discussed zirconia crowns risks. The ADA’s overview of materials for indirect restorations identifies chipping and fracture as recognized complications. The pattern varies by design: a veneered zirconia crown can chip in the more brittle outer porcelain, while a monolithic crown avoids a separate veneer layer but can still crack or fracture under unfavorable conditions.
These zirconia crowns risks are influenced by tooth preparation, minimum material thickness, sharp internal angles, unsupported ceramic, crown design, sintering, laboratory processing, adjustments, grinding, trauma, and bite forces. A high-strength label cannot compensate for inadequate clearance or an unbalanced bite. Conversely, removing excessive tooth structure merely to create space also carries biological cost.
Layered zirconia may offer optical advantages where nuanced translucency is important, but its veneer can create an additional interface. Monolithic zirconia can reduce veneer chipping concerns, yet appearance and surface finish still need careful management. Zirconia crowns risks are reduced by selecting the correct formulation and architecture rather than choosing “zirconia” as a single generic category.
4. Opposing-tooth wear and why polishing matters
One of the zirconia crowns risks patients sometimes hear about is that the restoration will “wear down” the tooth that bites against it. The concern is more nuanced. Surface roughness after chairside adjustment can matter greatly. A well-finished, polished zirconia surface behaves differently from one left rough after grinding. The ADA material review notes evidence that polished zirconia can be more wear-friendly to opposing tooth structure than feldspathic porcelain.
In practical terms, zirconia crowns risks increase when a restoration is adjusted but not restored to an appropriate polish, when the bite concentrates force on a small area, or when a patient clenches or grinds. Glaze alone may wear over time, so the underlying surface quality matters. The clinician should use finishing and polishing systems suitable for the specific zirconia and recheck contacts in normal and side-to-side movements.
Zirconia crowns risks related to bruxism do not automatically exclude a crown, but they change risk management. The plan may include bite adjustment, management of contributing factors, and a protective night appliance when clinically appropriate. A guard is not a guarantee; it must fit correctly, be maintained, and be reviewed for wear.
5. Debonding, cement failure, and crown removal
Among zirconia crowns risks, a crown can lose retention even when the ceramic remains intact. ADA reporting on clinician experience identifies debonding as a concern with zirconia restorations. Retention depends on preparation height and taper, available enamel and dentine, contamination control, the internal surface, the chosen cement or resin, pretreatment protocol, and following the material manufacturer’s instructions.
Zirconia crowns risks are not reduced by using the strongest cement in every situation without diagnosis. Some preparations have sufficient conventional retention; others may need an adhesive strategy. Saliva or blood contamination, incorrect cleaning after try-in, incompatible primers, or failure to observe curing and handling directions can weaken the interface. The dentist selects a protocol for the restoration and tooth rather than relying on a universal recipe.
Another of the zirconia crowns risks is removal difficulty: zirconia is strong and radiopaque, and the clinician must cut the crown while protecting the tooth or implant beneath it. This may increase chair time if retreatment, endodontic access, shade correction, or replacement is needed. Retrievability should be part of consent, especially on teeth with uncertain pulpal prognosis or restorations likely to require future access.
6. Marginal fit, gum irritation, and decay beneath a crown
Some zirconia crowns risks arise at the restoration-tooth interface. Zirconia does not decay, but the natural tooth at the crown margin can. A marginal gap, overhanging contour, deep margin, retained cement, or poor cleaning access can encourage plaque retention and gum inflammation. Recurrent decay may progress without being obvious to the patient until it becomes extensive. These are restoration-design and maintenance concerns, not evidence that zirconia itself causes cavities.
Among zirconia crowns risks, gum symptoms deserve early review. Bleeding, persistent tenderness, swelling, bad taste, or an unpleasant odor may reflect plaque, an ill-fitting margin, excess cement, periodontal disease, or another local issue. The clinician can assess the margin, contacts, crown contour, gum health, and radiographs when appropriate.
Fit-related zirconia crowns risks include a crown that is too bulky, making flossing difficult or compressing tissue. A contact that is too open may trap food; one that is too tight can obstruct cleaning. Good digital design and milling do not remove the need for clinical inspection. The crown should be checked on the actual tooth for seating, margin, contact, shade, and bite before final cementation.
7. Shade, translucency, opacity, and aesthetic limitations
Aesthetic zirconia crowns risks differ with translucency. Higher-translucency products can improve appearance but may have lower strength than more opaque, high-strength formulations. A dark stump, metal post, implant abutment, very thin crown, or demanding front-tooth shade can complicate the optical result. Layering may improve characterization but introduces potential veneer chipping.
Zirconia crowns risks in the aesthetic zone include a crown that appears too opaque, too bright, flat, or different under daylight and indoor lighting. Shade communication requires photographs, neighboring-tooth information, stump color, material thickness, and technician skill. A try-in can identify some concerns, but cement shade and hydration can influence the final appearance.
When zirconia crowns risks involve only a minor shade mismatch, replacement also has cost and biological implications. Cutting off a well-fitting crown may risk further tooth damage. Expectations should be discussed before preparation, including the realistic ability to match natural translucency, texture, and fluorescence.
8. Decision table: zirconia designs and alternatives
For zirconia crowns risks, this comparison organizes choices that may be discussed for a specific tooth. It is not a universal ranking or prescription.
| Restoration option | Potential advantage | Risk or limitation to discuss | Useful question |
|---|---|---|---|
| Monolithic zirconia crown | No separate veneering porcelain layer and high fracture resistance in suitable designs | Opacity, roughness after adjustment, debonding, and difficult removal | Which formulation, thickness, polish, and cement protocol will be used? |
| Layered zirconia crown | Can support more detailed surface characterization | Veneering ceramic can chip; framework opacity may remain | Where will layering be placed, and how will heavy contacts be managed? |
| Lithium-disilicate or another glass-ceramic crown | Often offers favorable translucency and adhesive options | Strength, thickness, and indication differ from zirconia | Does the bite and remaining tooth structure support this material? |
| Metal-ceramic crown | Long clinical history and a strong framework | Metal opacity, possible margin display, veneer chipping, and alloy considerations | How will appearance, alloy choice, and gum margin be managed? |
| Bonded onlay or direct restoration | May preserve more tooth structure in selected teeth | Not suitable for every pattern of damage or load | Can the tooth be restored predictably without full coverage? |
The best way to weigh zirconia crowns risks is to compare options for the same tooth, not generic material slogans. A high-load posterior tooth, a discolored front tooth, an implant, and a short bridge can require different formulations and designs.
9. Biocompatibility, allergy claims, and “toxicity” fears
Zirconia is widely used as a dental ceramic and FDA device documentation describes biocompatibility assessment for cleared zirconia materials. That supports their intended use when manufactured and processed according to instructions; it does not justify claiming that every crown system is “allergy-proof” or appropriate for every patient.
Concerns about zirconia crowns risks should include the whole restoration. Coloring liquids, veneering ceramics, stains, glaze, primers, resin cement, liners, core materials, posts, and implant components may be involved. A patient with a documented material allergy or previous unexplained oral reaction should provide that history so the dental team can review product information and, when necessary, coordinate specialist assessment.
Persistent burning, ulceration, swelling, or lichenoid changes should not be self-diagnosed as “zirconia toxicity.” Mechanical irritation, plaque, cement, infection, medication effects, and unrelated oral conditions can look similar. The appropriate response is a clinical examination and a differential diagnosis, not automatic removal of a crown based on an online claim.
10. How to reduce zirconia crowns risks before and after treatment
A risk-reduction plan begins before tooth preparation. The clinician should confirm diagnosis, control active disease, assess pulpal and periodontal prognosis, discuss alternatives, and record the bite. The laboratory prescription should state the tooth, material system, shade, thickness, margin, and design. Manufacturer instructions for preparation, processing, finishing, and cementation matter.
Use this checklist when discussing zirconia crowns risks:
- Ask why a full crown is recommended and whether a more conservative restoration is feasible.
- Discuss the tooth’s remaining structure, crack pattern, pulp status, gum support, and decay risk.
- Identify monolithic or layered construction and the specific zirconia formulation.
- Confirm required thickness, tooth reduction, margin location, and cleaning access.
- Ask how the restoration will be adjusted and polished if bite changes are needed.
- Review the cementation or bonding protocol and isolation requirements.
- Discuss appearance under different lighting and the limits of shade matching.
- Plan management of clenching, grinding, or an unstable bite.
- Arrange routine examinations and professional cleaning at personalized intervals.
- Report looseness, fracture, pain, swelling, or bite change rather than waiting.
At home, brush twice daily with fluoride toothpaste and clean between teeth or under bridge units as instructed. The World Health Organization identifies oral hygiene and tobacco use among important modifiable factors in oral disease. A crown protects a prepared surface but does not replace preventive care for the crown margin, gums, neighboring teeth, or the rest of the mouth.
If treatment abroad is being considered, request the material name, laboratory record, images, preparation and cementation summary, and follow-up plan. Through the Redent Klinik English contact page, you can ask what documentation and review schedule would apply to a proposed restoration; a final recommendation still requires clinical assessment.
Zirconia crowns risks: frequently asked questions
Do zirconia crowns risks include cracking or chipping?
Yes. Monolithic zirconia can fracture, although it is selected partly for fracture resistance. Layered zirconia can also experience chipping of the veneering ceramic. Risk depends on formulation, thickness, preparation, processing, adjustments, trauma, bite, and grinding. A material name alone cannot predict an individual outcome.
Do zirconia crowns damage opposing teeth?
A rough surface or poorly managed bite may increase opposing-tooth wear. Properly polished zirconia behaves differently from zirconia left rough after adjustment. The dentist should re-polish with an appropriate system, check contacts in multiple movements, and review heavy wear or grinding.
Can decay form underneath a zirconia crown?
The zirconia does not decay, but the natural tooth can develop recurrent decay at or beneath the margin. Risk relates to margin quality, plaque, diet, fluoride exposure, dry mouth, and attendance for review. New sensitivity, odor, food trapping, or gum bleeding warrants assessment.
Are zirconia crowns risks higher for people who grind their teeth?
Grinding can increase load on the crown, underlying tooth, opposing teeth, and jaw system. It may contribute to chipping, fracture, wear, debonding, or discomfort. The clinician should assess the bite and discuss risk management, which may include a protective appliance when suitable.
Can a zirconia crown fall off?
It can lose retention even without breaking. Preparation geometry, contamination, the internal surface, cement choice, protocol, decay, and force all matter. Keep the crown if it comes off, avoid chewing on the tooth, and contact a dentist promptly rather than gluing it yourself.
Are zirconia crowns toxic or likely to cause allergy?
Cleared zirconia dental materials undergo performance and biocompatibility evaluation for intended use. However, the complete restoration can include cements, primers, stains, ceramics, or other components. Persistent symptoms require clinical assessment; “hypoallergenic” or “zero reaction” claims should not replace an individual history and product review.
Why can a zirconia crown look too white or opaque?
Zirconia types differ in translucency, and the underlying tooth color, crown thickness, surface characterization, and cement can affect appearance. More translucent formulations may have different strength. Shade records, photographs, try-in, and laboratory communication help, but a perfect match cannot be guaranteed.
Is monolithic zirconia safer than layered zirconia?
It avoids a separate veneering porcelain layer, which can reduce one chipping interface, but it has its own aesthetic, surface, retention, and removal considerations. Layering may improve characterization yet can chip. “Safer” depends on tooth position, load, design, thickness, and patient priorities.
Can a zirconia crown be removed or repaired?
Removal is possible but may be technically demanding because the material is strong. Limited chips or access openings may sometimes be managed with repair protocols, while other problems require replacement. The dentist must assess the cause, remaining tooth, margin, bite, and feasibility of a durable repair.
When should I seek urgent help for a crown problem?
Arrange prompt dental care for a loose crown, sharp fracture, increasing pain, swelling, discharge, bad taste, or a bite that suddenly feels wrong. Seek urgent medical assessment for rapidly spreading facial swelling, difficulty breathing or swallowing, uncontrolled bleeding, or systemic illness.
Final perspective: material strength does not remove clinical risk
Zirconia crowns risks are best understood as interactions among the tooth, gums, bite, restoration design, ceramic formulation, laboratory process, surface finish, cementation, and maintenance. Zirconia can be a strong and useful option, but strength cannot compensate for an unsuitable tooth, inadequate space, rough adjustment, poor fit, uncontrolled disease, or absent follow-up.
Ask for the actual material and design rather than a marketing label. Compare conservative alternatives, monolithic and layered zirconia, glass-ceramic, metal-ceramic, and other suitable options for the same tooth. A good consent discussion explains expected benefits, realistic limitations, uncertainty, maintenance, and what would happen if the crown needs repair, endodontic access, or replacement.
This article provides general education, not a diagnosis or personal treatment recommendation. A qualified dentist who has examined the tooth can determine whether a crown is indicated and which material is appropriate. Do not delay assessment of persistent pain, swelling, looseness, or gum changes because a restoration appears intact.
Authoritative sources
- American Dental Association and its Materials for Indirect Restorations review — zirconia formulations, mechanical properties, wear, complications, and clinical evidence.
- World Health Organization oral health fact sheet — oral disease prevention, hygiene, tobacco, diet, and lifelong care.
- ADA MouthHealthy crown overview — reasons crowns are used on natural teeth and implants.
- Leeds Teaching Hospitals NHS Trust crown guidance — suitability, tooth preparation, material choices, alternatives, and maintenance.
- US FDA 510(k) summary for a contemporary zirconia dental material — intended use, processing, ISO ceramic standards, performance testing, and biocompatibility assessment.