
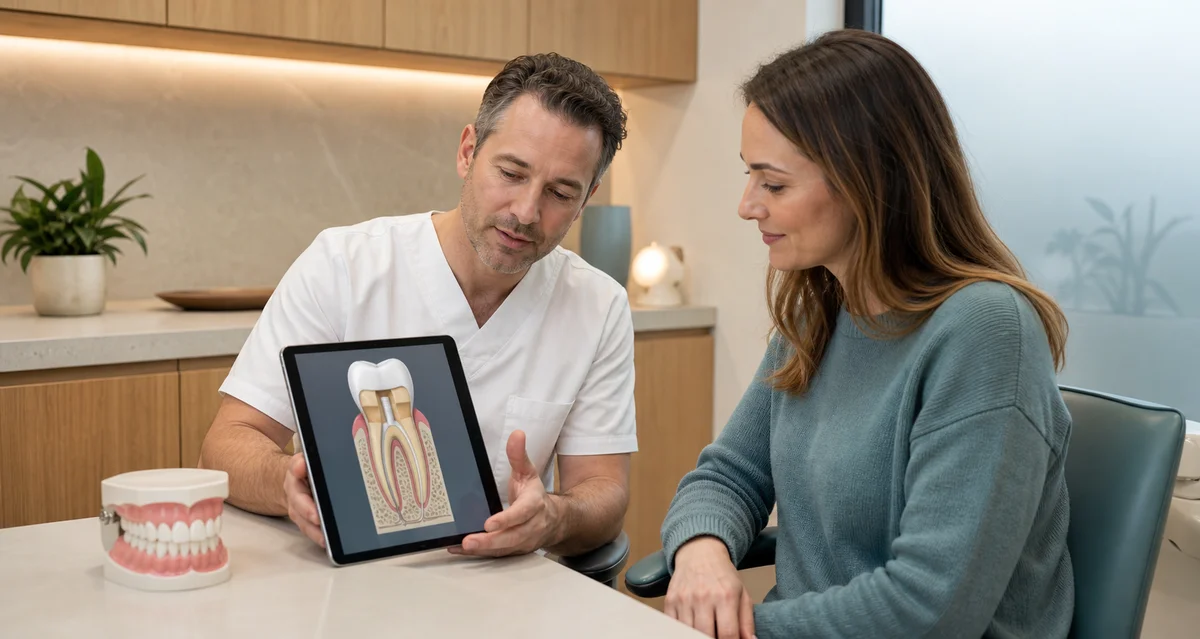
Dental post and crown cost is not a single standard fee because “post and crown” describes several possible stages, not one identical product. The total may involve diagnosis, an existing or new root-canal treatment, post-space preparation, a post, core buildup, temporary protection, a laboratory or chairside crown, fitting and follow-up. It can also change if decay, a crack, gum disease or an inadequate old root filling alters whether the tooth is restorable.
Quick answer: Dental post and crown cost depends on whether root-canal treatment is complete and healthy, how much sound tooth remains, whether a post is actually required, post and core technique, crown material, laboratory method, specialist involvement, temporary care, follow-up and insurance rules. Request a written, itemized estimate after examination; the post, core, root canal and crown may be billed separately.
This patient guide explains how to compare a complete treatment pathway without naming a fixed price, diagnosing a tooth remotely or guaranteeing survival. A post is not routinely needed in every root-treated tooth, and placing one removes additional internal tooth structure. A crown is also not suitable for every broken or infected tooth. Restorability, periodontal support, crack pattern, remaining walls, bite and alternatives should be assessed before irreversible treatment.
1. What dental post and crown cost actually describes
A dental post is a narrow restorative component placed inside part of a root canal in a tooth that has already received root-canal treatment. Its purpose is to help retain a core when insufficient natural structure remains to hold that core. The core rebuilds the missing central portion of the tooth. The crown is the outer cap fitted over the prepared tooth and core.
These three elements should not be confused. The post does not replace root-canal filling, and it is not an implant. The core is not the final crown. The crown covers the visible prepared structure, while a dental implant replaces a missing root and follows a different surgical and restorative pathway. An accurate dental post and crown cost quote names each component.
The American Association of Endodontists’ restorative standards state that a post is used when the remaining tooth structure cannot retain the core. They also caution that posts do not inherently improve tooth survival and may be unnecessary when adequate supporting dentine walls remain. Therefore, “post included” is not automatically a benefit; it needs a clinical reason before it is added to dental post and crown cost.
2. When is a post needed before a crown?
The need depends mainly on how much sound tooth remains after decay, old restorations and unsupported material are removed and after crown preparation is considered. Tooth type, wall distribution, access-cavity size, previous fracture, root anatomy, planned core material and loading also matter. A front tooth with extensive loss and a back tooth with several intact walls are not equivalent.
A post may help retain a core in a severely broken-down root-treated tooth. It does not reinforce every tooth, cure a crack, treat infection or replace missing bone support. Preparing space for a post involves removing some root-filling material and may involve additional dentine removal, so the benefit should outweigh procedural risks. Necessity, not a package, should determine dental post and crown cost.
Ask the dentist to show which walls remain and why the core would not be retentive without a post. If the answer is uncertain before an old crown is removed, the estimate can present the post as a contingent item. This distinction makes dental post and crown cost transparent rather than automatic.
3. Decision table for dental post and crown cost
| Starting situation | Key planning question | Possible separate services | Quote question |
|---|---|---|---|
| Root canal complete; several sound walls remain | Can the core retain without a post? | Core, provisional and crown | What finding makes a post necessary or unnecessary? |
| Root canal complete; tooth severely broken down | Is enough ferrule and root support available? | Post, core, crown and possible gum treatment | How is restorability confirmed before post preparation? |
| Active pain or unresolved infection | Is primary treatment or retreatment needed? | Endodontic assessment, imaging, treatment and temporary seal | Is the root-canal stage included? |
| Old post and crown have failed | Can they be removed safely and is the root intact? | Removal, retreatment, new post/core or alternative | What is payable if a fracture is found? |
| Decay or fracture below the gumline | Can a maintainable restoration margin be created? | Crown lengthening or orthodontic extrusion | Are periodontal or orthodontic stages separate? |
| Tooth judged non-restorable | What are the risks of retention versus removal? | Extraction and later replacement planning | How are unused post-and-crown fees handled? |
The table is a comparison aid, not a diagnostic tool. A quote for a healthy root-filled tooth with sufficient structure is different from a quote involving retreatment, post removal or periodontal surgery. Scope must match before two dental post and crown cost figures can be compared.
4. Examination, imaging and restorability
Planning usually begins with symptoms, dental history, previous root-canal records, medical conditions, medicines, allergies, tobacco use and the patient’s goals. The dentist may assess remaining tooth structure, decay, cracks, existing restorations, tenderness, mobility, gum health, bone support, tooth position and bite. A photograph cannot reveal every decisive feature.
Clinically justified X-rays can help assess the root filling, root shape, post space, bone and signs requiring further evaluation. In selected cases, additional imaging or an endodontic opinion may be appropriate. Recent diagnostic-quality records may sometimes be transferred, but the treating clinician decides whether they answer the current question and how they affect dental post and crown cost.
Restorability comes before dental post and crown cost. A post and crown cannot predictably rescue every vertical root fracture, deeply extending crack, severe decay, unfavourable root form or tooth with inadequate support. The clinician should explain prognosis, uncertainty and what happens financially if hidden damage becomes visible only after an old restoration is removed.
5. Root-canal treatment may be a separate stage
A post is placed only in a tooth that has undergone root-canal treatment, but the root-canal service may already be complete, newly required or in need of reassessment. The NHS explains that root-canal treatment removes infected pulp, cleans and shapes the internal space, fills and seals it, often with a temporary restoration between stages. A crown may later protect a badly damaged tooth.
Primary endodontic treatment varies with tooth type, canal anatomy, infection, access, imaging and whether a specialist is involved. Treatment is not interchangeable with the final post, core and crown. Ask which provider completes each stage and whether the restorative dentist has confirmed enough structure for the final plan before accepting dental post and crown cost.
If root-canal treatment is not included, a low dental post and crown cost can understate the total pathway. Request separate estimates and the intended sequence. Urgent drainage, temporary filling, prescribed medicines when clinically indicated and follow-up may also have distinct charges; they should not be assumed from the crown fee.
6. Endodontic retreatment and post removal
A previously treated tooth can become symptomatic or diseased if anatomy was missed, the seal was delayed, new decay develops, a restoration leaks or the tooth fractures. The AAE explains that retreatment can require reopening the tooth, removing earlier materials, locating additional anatomy, cleaning, refilling and resealing before a definitive restoration.
An existing post may obstruct access. Removing it can demand specialised instruments and expertise, and it carries risks that depend on post type, cement, length, root anatomy and remaining dentine. In some situations, another endodontic approach or extraction may be discussed. No remote estimate can decide the safest route or final dental post and crown cost.
Retreatment and post removal can substantially change dental post and crown cost. Ask whether the quote covers diagnostic assessment, removal attempts, temporary sealing, new post/core, definitive crown and contingency if the root cracks or the post cannot be removed safely. Consent should occur before extra work begins.
7. Fibre, metal, cast and prefabricated post options
Posts may be fibre-reinforced, metal or other dental materials and can be prefabricated or custom made. Selection depends on remaining tooth, canal shape, retention, space, crown material, aesthetic demands, removal considerations and the clinician’s judgement. Marketing labels such as “premium fibre” do not establish suitability.
A prefabricated post may be combined with a separate core buildup. A custom cast post and core can involve a laboratory stage and different preparation. Technique, isolation, cementation, verification and possible temporisation affect the appointment plan. The post material is only one part of clinical complexity and one component of dental post and crown cost.
Material can influence dental post and crown cost, but a more expensive post is not automatically safer. Ask why that design fits the root and remaining tooth, how much internal structure must be removed, what future removal might involve and whether an adequate core could be retained without a post.
8. Core buildup, ferrule and remaining tooth structure
The core replaces missing coronal structure and creates the form that supports crown preparation. Its material and placement depend on the tooth and restorative plan. The amount and distribution of sound natural tooth around the prepared core—often discussed in relation to ferrule—are important to resistance and prognosis. A post cannot compensate for every lack of sound tooth.
If decay or fracture extends too far below the gumline, crown lengthening or orthodontic extrusion may be considered to expose maintainable structure. Both add appointments, biological considerations and cost. Sometimes the effect on the root, bone, gumline or neighbouring tissues makes extraction a more reasonable option than proceeding with the quoted dental post and crown cost.
An itemised dental post and crown cost should list the core separately when local billing practice treats it as a distinct service. It should state whether the core is confirmed and whether periodontal or orthodontic treatment remains possible. Ask for the complete route to a cleanable final margin.
9. Crown material and laboratory work
The definitive crown may be made from ceramic, metal alloy, porcelain fused to metal or another dental material. Choice depends on tooth position, available space, bite forces, opposing teeth, remaining structure, appearance and other clinical factors. The most cosmetic material is not automatically appropriate for every load or preparation.
Laboratory fees can reflect design, technician time, material, shade communication, quality checks and the chosen workflow. Front teeth may require extra photographic records or custom shade work. A temporary crown may protect the prepared tooth while a laboratory fabricates the final restoration, and these services should be identified in dental post and crown cost.
The crown portion of dental post and crown cost should identify the material and whether laboratory, provisional, fitting, bite adjustment and routine review are included. “Ceramic crown” alone may not reveal enough for comparison. Ask how remakes or adjustments are handled and which conditions apply.
10. Conventional and same-day restorative workflows
A conventional workflow may include post preparation and core buildup, crown preparation, an impression or scan, a temporary crown, laboratory fabrication and a later fitting visit. Post, core and crown do not always need to occur in one appointment. The timing may depend on endodontic status, tissue health and certainty about prognosis.
A chairside digital workflow may produce a crown in the practice for selected cases. It can reduce temporary wear or a routine second visit, but it does not remove the need for diagnosis, post selection, core, isolation, preparation and quality assessment. Some aesthetic or complex cases can benefit from laboratory technician input, which makes workflow relevant to dental post and crown cost.
Same-day language does not automatically lower dental post and crown cost or improve outcomes. Compare the included services, material, temporary contingency, adjustment support and suitability. Biological healing after endodontic or periodontal treatment should not be compressed merely to match a one-visit package.
11. Temporary protection and appointment sequence
After root-canal treatment or while a definitive crown is being made, the tooth may have a temporary filling, core or crown. The AAE advises protecting the treated tooth and completing the final restoration promptly according to the clinician’s plan. A temporary is not designed to be an indefinite substitute.
Temporary recementation, repair or adjustment may be included for a stated period or charged separately. If it becomes loose, breaks or the bite feels wrong, contact the clinic rather than gluing it at home. Avoid using the tooth for hard biting until the treating team says the restoration is complete. Temporary-care terms belong in dental post and crown cost.
The appointment sequence belongs in dental post and crown cost: diagnostic visit, endodontic stage, post/core, preparation, provisional, laboratory time, fitting and review. Ask which visits require local anaesthesia, how long the quote remains valid and what happens if travel or healing delays the final crown.
12. Clinician, specialist and facility fees
A general dentist may complete post, core and crown care, while an endodontist may assess or treat complex root-canal disease. Periodontists, prosthodontists or oral surgeons may contribute when gum, restorative or extraction issues are complex. Separate providers may issue separate estimates and invoices.
Fees can reflect professional time, team training, sterilisation, regulated materials, digital equipment, laboratory arrangements, emergency readiness, premises and professional obligations. Sedation, if clinically appropriate, requires assessment, monitoring and trained personnel and may involve a separate provider or facility. It is distinct from routine local anaesthesia and can change dental post and crown cost.
Provider and setting influence dental post and crown cost, but a low fee does not prove value and a specialist fee does not prove unnecessary complexity. Verify professional registration, diagnosis, scope and continuity. Ask who manages urgent problems at each stage and who holds responsibility for the definitive restoration.
13. Risks and limitations to understand before paying
Possible procedural problems include perforation, post loosening, cement failure, core fracture, crown fracture, recurrent decay, gum inflammation, sensitivity in surrounding tissues, root fracture or persistent endodontic disease. Removing tooth structure for a post or crown is irreversible. Risks vary with anatomy, damage and technique.
A crown can cover and protect a prepared tooth, but it does not make the root immune to fracture or infection. The crown margin can still develop decay, and gum health still needs maintenance. A post can retain a core, but it cannot repair a vertical root fracture or guarantee survival. Those limitations should be explained alongside dental post and crown cost.
A meaningful dental post and crown cost discussion includes prognosis, risks, alternatives, uncertainty and the consequences of no treatment. No clinician should promise lifetime survival. Ask which routine adjustments are covered, what constitutes a laboratory remake and which biological complications are outside any policy.
14. Dental insurance and patient balance
Dental benefit plans may classify root-canal treatment, post, core and crown as different services. Deductibles, coinsurance, annual maximums, network status, allowed amounts, waiting periods, replacement-frequency rules and prior authorisation can affect the balance. Coverage of one stage does not imply coverage of all stages.
Ask the clinic for proposed procedure codes, tooth number, narrative and supporting records. Ask the insurer how each component is processed, how much annual maximum remains and whether a less costly alternative provision applies. A pre-treatment estimate can help, but it is often not a payment guarantee and can change the final dental post and crown cost with eligibility or clinical findings.
Insurance-adjusted dental post and crown cost should separate the clinic’s fee, the plan’s estimated allowed amount, estimated plan payment and estimated patient share. Avoid relying on a percentage alone. The denominator, exclusions and annual maximum determine what that percentage actually means.
- Is the root-canal treatment new, complete or under reassessment?
- Are post and core separate covered services?
- Does the crown have a waiting or replacement-frequency rule?
- Do deductible and coinsurance apply to each stage?
- How much annual maximum remains now?
- Are the dentist, endodontist and laboratory in network?
- Is prior authorisation or additional documentation required?
- Is the plan response binding or only an estimate?
15. Medicare, Medicaid and Marketplace coverage
In the United States, Original Medicare generally excludes care connected with teeth and the structures directly supporting them. The Centers for Medicare & Medicaid Services describes limited circumstances in which dental services are inextricably linked to specified Medicare-covered medical care. Those exceptions do not create routine coverage for a post and crown. Some Medicare Advantage plans add dental benefits.
Adult Medicaid dental benefits vary by state because states have flexibility and there is no federal minimum adult dental requirement. Covered-service lists, authorisation, network rules and limits may apply. The current state programme or managed-care plan must evaluate the actual procedures rather than the phrase “post and crown.”
HealthCare.gov explains that adult dental coverage is not an essential health benefit in Marketplace plans. Benefits may be embedded in a health plan or offered through a separate dental plan, and stand-alone coverage can have a waiting period. Public-programme rules can change dental post and crown cost for an individual, but only the relevant administrator can confirm benefits.
16. Itemized checklist for dental post and crown cost
A useful written estimate identifies the tooth, diagnosis or rationale, providers, confirmed services, possible additions, billing currency, deposit and validity period. It should explain what happens if hidden decay, a crack or an inadequate root filling changes the plan. A verbal “all included” promise is not a substitute for an itemised dental post and crown cost.
Use this checklist to compare dental post and crown cost:
- Consultation, examination and clinically justified X-rays.
- Primary root-canal treatment or endodontic retreatment.
- Removal of an old crown, core or post when required.
- Post-space preparation and named post technique.
- Core buildup and any separate foundation procedure.
- Crown lengthening, gum treatment or orthodontic extrusion.
- Crown preparation, scan or impression and named material.
- Laboratory or chairside manufacturing charge.
- Temporary filling or crown and recementation terms.
- Definitive fitting, cementation, bite adjustment and review.
- Specialist, sedation or facility fee when applicable.
- Emergency support, remake and cancellation conditions.
- Estimated insurance payment and remaining patient balance.
- Contingency if the tooth is found non-restorable.
Confirm which items are included, excluded or dependent on findings. One quote may appear higher because it includes root-canal treatment and temporary care, while another begins only after those stages. Complete itemisation makes dental post and crown cost comparable.
17. Dental travel and complete budgeting
Travelling for care adds transport, accommodation, meals, time away from work, record transfer and contingency visits. A photograph or old X-ray may support an initial conversation, but cannot confirm a crack, current endodontic status, root anatomy, remaining sound dentine or periodontal support. Treat pre-travel figures as provisional.
Ask how many visits are expected, whether different specialists are involved, how long the temporary must be worn, who fabricates the crown and who manages pain or a loose temporary after returning home. Retreatment or gum surgery may require intervals that should not be compressed to suit flights, and travel contingencies belong in dental post and crown cost.
At Redent Klinik, treatment planning is individual and based on the tooth’s condition. The English contact page can be used to ask which existing records may support preliminary planning and how a provisional dental post and crown cost estimate is structured. Travel coordination is not diagnosis, consent or an outcome guarantee.
18. Alternatives to a post-and-crown pathway
If enough sound structure remains, a core or another restoration without a post may be possible. Depending on the tooth, an onlay, direct restoration or crown without a post may be considered. If the margin is deep, orthodontic extrusion or crown lengthening may be alternatives within a tooth-retention plan.
If the tooth has an unfavourable fracture, insufficient support or disease that cannot be treated predictably, extraction and replacement options may be discussed. An implant, bridge or removable prosthesis has a different timeline, risk profile and total budget. Leaving a space or monitoring also has consequences that should be explained before choosing solely by dental post and crown cost.
Compare clinically reasonable pathways rather than only dental post and crown cost. Ask for separate estimates, likely appointment sequences, maintenance and the prognosis of keeping the tooth. For complex non-urgent care, an independent second opinion can support informed consent.
19. Frequently asked questions about dental post and crown cost
Can dental post and crown cost be quoted from a photo?
A photo cannot confirm remaining internal structure, root filling quality, cracks, decay depth, bone support or post-space anatomy. A clinic may describe consultation fees and scenarios, but the definitive scope needs examination and appropriate records. Treat remote figures as provisional and ask what findings can change them.
Does every root-canal tooth need a post?
No. The AAE’s restorative standards indicate that a post is needed when remaining structure will not retain the core; adequate supporting walls can make a post unnecessary. Tooth type and distribution of tissue loss matter. Ask the dentist to explain the retention problem the post is intended to solve.
Does dental post and crown cost include root-canal treatment?
Not necessarily. Root-canal treatment, post, core and crown can be separate services delivered by different clinicians. Ask whether the root filling is already considered adequate, needs primary treatment or requires retreatment. Obtain a written estimate for each stage and a combined treatment sequence.
Is a fibre post always better than a metal post?
No material is automatically best for every tooth. Root anatomy, remaining dentine, retention, crown design, aesthetics, technique and future removal considerations influence selection. The clinician should explain why the proposed post suits the case and whether a post is needed at all.
Can a post strengthen a root-treated tooth?
A post primarily retains a core when natural tooth structure is insufficient. It should not be presented as universal reinforcement. Preparing post space can involve removal of internal material and carries risks. The restorative plan should conserve sound structure while providing adequate retention.
What if an old post must be removed?
Removal can be complex and depends on post type, cement, length, root anatomy and remaining dentine. An endodontic assessment may be appropriate. Ask about the removal fee, alternatives, temporary sealing and contingency if the post cannot be removed safely or a root fracture is found.
Does insurance cover dental post and crown cost?
Coverage depends on the plan and documentation. Post, core, root canal and crown may have different deductibles, coinsurance, limits or authorisation rules. Request a pre-treatment estimate using the tooth number and proposed codes, but do not treat estimated payment as guaranteed.
How many visits are needed for a post and crown?
The number varies with endodontic status, post technique, laboratory or chairside crown method, tissue health and complications. A straightforward restorative phase may take fewer visits than retreatment with specialist care. Ask for the planned sequence and the conditions that could add appointments.
How long will a post and crown last?
No exact lifespan is guaranteed. Outcome depends on diagnosis, remaining structure, root and gum health, bite, material, fit, hygiene, diet, dry mouth, habits and accidents. Regular care and prompt review of symptoms matter, but even well-maintained treatment can require repair or replacement.
What warning signs require prompt dental advice?
Contact a dentist for increasing pain, swelling, fever, a loose temporary or crown, a bite that suddenly feels wrong, discharge, fracture or the return of previous symptoms. Severe facial swelling with breathing or swallowing difficulty and other medical emergencies require urgent emergency care.
20. Patient-safe takeaway
The reliable dental post and crown cost begins with one question: can the tooth be restored predictably, and how much sound structure remains? Then align root-canal status, need for a post, core, gum treatment, crown material, laboratory, temporary care, providers, reviews and insurance. Prices are comparable only when scope matches.
Request a written, itemised and time-limited estimate that distinguishes confirmed work from contingencies. Ask why a post is needed, what alternatives exist and what happens if hidden decay, infection or fracture changes the plan. Patient safety, conservation of tooth structure and a maintainable restoration matter more than the lowest headline.
Authoritative sources
- American Dental Association — professional standards and oral-health information.
- ADA MouthHealthy: Root canals — root-canal stages, definitive restoration and possible post context.
- American Association of Endodontists: Standards in Restoration of Endodontically Treated Teeth — role and indications of posts and final restoration.
- American Association of Endodontists: Endodontic retreatment — reasons and general pathway for retreatment.
- NHS: Root-canal treatment — treatment stages, temporary care and possible later crown.
- Centers for Medicare & Medicaid Services: Medicare dental coverage — current dental exclusion and limited medically linked circumstances.
- Medicaid.gov: Dental care — state flexibility in adult dental benefits.
- HealthCare.gov: Dental coverage — Marketplace adult dental benefits and possible stand-alone-plan waiting periods.
- World Health Organization: Oral health — global oral-disease, prevention and access-to-care context.
Clinical and U.S. coverage sources were checked on 23 August 2026. Treatment recommendations, benefit rules and plan terms can change; confirm current details with the relevant authority, insurer and treating clinicians.