
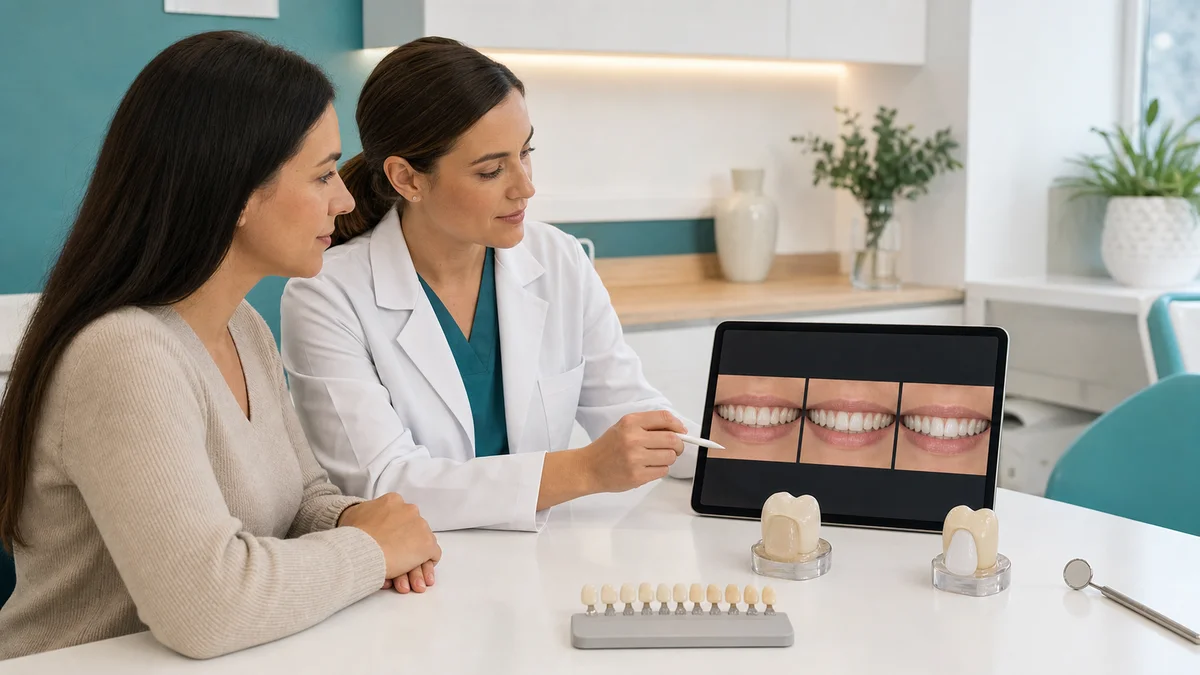
Quick answer: Read veneers before and after images as a map of changes, not a promise. Check colour, edge position, tooth width, spacing, symmetry, gum frame, surface texture and the number of treated teeth. Then ask whether whitening, orthodontics, gum treatment, composite, porcelain or crowns contributed. A reliable plan also documents enamel preparation, bite, cleaning access, provisional stages and a settled review.
A striking “after” smile can contain more dentistry than the caption reveals. The visible change may come from veneers alone, or from cleaning, whitening, gum treatment, orthodontics, replacement of old fillings, contouring and professional photography. Unless the full sequence is disclosed, it is impossible to know which part of the image a veneer actually produced.
The most useful veneers before and after analysis therefore works backwards. Instead of asking, “Can I have this smile?”, ask, “Which clinical changes are visible, which are hidden, and what treatment created each one?” That approach protects healthy tooth structure and helps separate a realistic personal plan from an attractive but incomplete gallery result.
This guide explains composite and porcelain veneers, mock-ups, provisional restorations, settled outcomes and combined treatment. It does not diagnose suitability from a photograph. Veneers are dental treatment, and the decision requires examination of teeth, gums, enamel, bite, habits, expectations and the ability to maintain the result.
veneers before and after images may show more than veneers
A veneer covers the front surface of a tooth, unlike a crown that surrounds more of the tooth. The ADA’s patient resource on dental veneers describes porcelain as a custom-made shell and composite as tooth-coloured material bonded and sculpted on the tooth. The same resource warns that enamel may be removed and that veneer treatment is not reversible in that context.
A broad, evenly coloured smile in an “after” photo may reflect several interventions:
- Professional cleaning: removes deposits and some external stain before colour is judged.
- Whitening: lightens responsive natural teeth that are not covered by restorations.
- Orthodontics: changes tooth position, rotation, spacing and sometimes the gum outline.
- Gum or periodontal care: treats inflammation or changes the visible tissue frame.
- Composite bonding or veneers: adds tooth-coloured material directly and is polished in the mouth.
- Porcelain veneers: uses laboratory- or digitally fabricated shells bonded to prepared teeth.
- Crowns: may be used on structurally compromised teeth but are not the same as veneers.
- Photography: lighting, retraction, lip posture, camera settings and dehydration alter appearance.
A caption that says “ten veneers” should clarify whether ten teeth were restored and whether other teeth were whitened. A result labelled “no-prep” should explain whether enamel was altered at all, whether old restorations were removed and whether the teeth had already been reduced. Marketing terms do not replace a tooth-by-tooth treatment record.
Eight changes to decode in the visible result
1. Colour value and uniformity
Colour is more than “white.” Natural teeth show variations in brightness, saturation, translucency and character. A very bright exposure can hide these differences. Ask whether the shade was recorded under consistent lighting and whether neighbouring natural teeth were whitened before the veneer shade was selected.
2. Incisal edge position
The incisal edge is the biting edge of a front tooth. Lengthening it can change how much tooth shows at rest, during speech and in a full smile. An image may show a pleasing longer edge, but only clinical and video assessment can reveal whether it affects sounds, lip movement or bite contacts.
3. Width-to-length proportion
Veneers can alter apparent proportions by adding to edges or sides. A frontal photograph may make wide teeth look balanced when the camera is positioned differently. Compare central and lateral incisors, transitions between teeth and whether added width has closed spaces without making the teeth bulky.
4. Spacing and apparent alignment
Veneers can close selected gaps and mask some shape or position differences, but they do not move roots through bone. If significant crowding or rotation appears “straight” after restorations, ask how much material was added and removed. Orthodontics may offer a more conservative route in some cases.
5. Symmetry and dental midline
Small natural asymmetries are common. A perfectly mirrored image may look artificial or may reflect editing. Check whether the centre line between the upper front teeth relates naturally to the face and whether the left and right teeth are harmonised without becoming identical copies.
6. Gum frame
Healthy gums shape the visible borders of veneers. Redness, bleeding, recession, uneven margins or excess material near the gum can affect the final appearance and cleanability. Immediate post-placement tissue may be irritated; a settled review is more informative than a same-day close-up.
7. Texture, translucency and reflection
Surface texture breaks up reflected light, while translucency and internal effects influence depth. A ring light can make a flat surface look glossy and erase texture. Close, polarised and side-lit records may reveal features that a frontal social-media photograph cannot.
8. Treatment scope
Count the teeth that changed. If the “after” image displays a broad smile but only six restorations were placed, how were the side teeth handled? If every visible tooth looks identical, were more teeth treated than the caption suggests? A written chart is more reliable than guessing from pixels.
Composite veneers and porcelain veneers create different pathways
Direct composite is applied, shaped, cured and polished on the tooth, often in one or a small number of appointments. Porcelain veneers are indirect restorations made outside the mouth from an impression or scan, tried in and bonded. The ADA’s overview of indirect restorative materials notes that indirect restorations involve material and bonding choices with different aesthetic, strength and durability considerations.
Neither route is universally more conservative. Composite may allow an additive approach in a suitable shape problem, but finishing, polishing and later removal can still alter enamel. Porcelain may permit thin, stable restorations in a carefully selected plan, yet usually requires a defined preparation and irreversible commitment. The starting tooth determines what “minimal” means.
| Decision area | Direct composite veneer | Porcelain veneer | Question for the plan |
|---|---|---|---|
| How it is made | Sculpted and polished directly on the tooth | Fabricated indirectly from a scan or impression | Who designs, makes and finishes it? |
| Tooth preparation | May be additive or require contouring, depending on the tooth | Often requires planned enamel preparation | Show the expected reduction tooth by tooth. |
| Repair | Can often be repaired or modified directly | Small adjustments are possible; fracture may require remaking | What is the repair pathway away from the clinic? |
| Surface over time | Can stain, wear or lose polish and may need maintenance | Colour-stable ceramic surface but still subject to chipping or debonding | Which changes are expected, and how are they managed? |
| Preview | Trial additions may help demonstrate shape in selected cases | Wax-up, mock-up and provisionals may test form before final bonding | Which stage can still be changed without committing? |
| Maintenance | Review of polish, margins, bite and repairs | Review of margins, bonding, ceramic integrity and bite | What is included and what is chargeable later? |
This comparison does not predict longevity. Material performance depends on enamel available for bonding, preparation design, isolation, bite, tooth grinding, diet, oral hygiene, clinician and technician skill, and the size and position of the restoration. A material name is not a guarantee.
“No-prep” and “reversible” need tooth-specific evidence
“No-prep” is often used as if it were a product category with a fixed biological cost. In reality, suitability depends on the starting tooth position, shade, existing restorations, contour and desired result. Adding a shell to a tooth that is already prominent can create excessive bulk or a difficult gum margin. Dark colour may require thickness or another strategy to avoid an opaque result.
Ask for a diagram or digital record showing whether enamel will be polished, roughened, reduced at the edge or sides, or altered near the gum. Ask whether contacts between teeth will be opened and whether existing composite will be removed. Even a small irreversible change should be included in consent.
The General Dental Council’s April 2026 discussion of composite bonding complaints and concerns cautions against oversimplifying reversibility: complete removal of composite without altering enamel can be difficult. The article is professional insight rather than a universal clinical rule, but it supports asking for honest, material-specific explanations.
A reversible mock-up is not the same as reversible definitive treatment. A temporary trial placed over unprepared teeth may be removed, while the final bonded restoration may follow enamel preparation. The consent discussion should distinguish these stages.
Understand the five photo stages
Not every “after” is final. A patient may see several visually convincing stages, and each answers a different question.
- Baseline: documents the untreated or pre-restorative condition, including existing fillings, wear, colour and gum health.
- Diagnostic design: a digital image or wax-up proposes tooth shapes; it is a planning hypothesis, not a biological outcome.
- Mock-up: a removable or temporary material transfers the proposed shape to the mouth so appearance, speech and length can be tested.
- Provisional restoration: protects prepared teeth and tests contours while final indirect restorations are made; it is not the final material.
- Settled final review: records bonded restorations after tissues and tooth hydration have stabilised and bite adjustments have been checked.
A mock-up can look thick because it sits over the existing tooth. A provisional can have different surface and optical qualities from the final porcelain. A same-day final photograph may show temporary gum blanching, retraction marks or dehydration. The caption should identify the stage and timing.
A frontal smile cannot show function
Veneers participate in speech, biting and the guidance of jaw movement. Still photographs do not show how front teeth contact during chewing or how the lower jaw moves side to side. They also cannot show clenching forces, sleep grinding, a deep overbite or the amount of enamel behind the restoration.
Before treatment, the assessment may include bite records, movement patterns, tooth wear, jaw symptoms, existing fractures and habits. In some patients, orthodontics, protective splint therapy, repair of posterior teeth or another step may be discussed before veneers. A night guard does not correct a poor restoration design, but it may be part of risk management for selected patients.
After placement, report a bite that feels high, a new interference, persistent difficulty speaking, a sense of excessive bulk, pain on biting or repeated chipping. Early review may allow adjustment. Continuing to “get used to” a persistent functional problem without assessment can allow damage.
Gum health and cleaning access belong in the after result
The visible margin between a veneer and gum must be smooth, cleansable and compatible with healthy tissue. Inflamed gums can bleed during records, change shape and reduce the accuracy of impressions or scans. The ADA advises treating decay and gum disease before veneers because placing restorations over unhealthy teeth can worsen existing problems.
An immediate photograph cannot prove long-term tissue health. Ask for review after healing and for instruction on brushing and cleaning between treated teeth. Closed spaces, overhanging material and bulky contours can trap plaque. A pleasing outline is not sufficient if floss cannot pass appropriately or the patient cannot maintain the margin.
Gum recession can expose a veneer edge or root over time. Risk varies with tissue type, brushing trauma, periodontal health, margin position and other factors. The plan should discuss what can change and whether repair, replacement, periodontal treatment or observation would be considered.
Photography can change perceived tooth shape and shade
Camera distance, lens choice, head posture and smile effort affect proportion. A close wide-angle phone image can enlarge central teeth relative to the sides. Tilting the head changes the apparent smile line. Lip retraction exposes more tooth than a natural social smile. These differences can make treatment appear more extensive or more symmetrical.
Lighting affects colour and texture. A ring light can produce uniform reflections; cross-polarised photography can reduce surface glare; warmer white balance can make teeth look creamier; increased exposure can erase surface features and make gums look pale. Both records should use similar settings if the goal is comparison.
Simple image checks include:
- same facial or intraoral view, camera distance and head position;
- similar lip posture, retraction and tooth moisture;
- consistent lighting direction, exposure and white balance;
- no beauty filter, skin smoothing or selective tooth brightening;
- clear treatment stage and time since placement;
- disclosure of whitening, orthodontics, gum procedures and other restorations;
- patient consent for taking and promotional use of the images.
These checks do not prove clinical quality. They make the visible comparison less ambiguous and help prevent an image from creating an unjustified expectation.
Consent applies to treatment and photographs separately
Agreeing to clinical photographs for records does not automatically mean agreeing to public marketing. The GDC’s patient-information FAQ states that consent is needed both to take photographs and to use them to promote a practice. It also says patients should understand how images will be used, that consent should be recorded, and that the minimum necessary information should be released.
Local privacy rules differ, but the practical questions are broadly useful: Where will the image appear? Will the face be identifiable? Can it be reused in paid advertising? How long will it remain online? What happens if consent is withdrawn? Refusing public use should not reduce the quality of care.
Clinics also have a duty not to create misleading expectations. The GDC’s guidance on advertising calls for current, factual, unambiguous information and warns against claims likely to create unjustified expectations. A gallery should show what was done and acknowledge that results vary.
Suitability is decided before design
Veneers may be considered for selected shape, colour, surface, wear or spacing concerns, but suitability is not diagnosed from a selfie. Examination should establish whether teeth are healthy, whether there is sufficient enamel for bonding, whether decay or cracks are present, and whether gum disease, erosion or grinding changes the risk.
Alternatives may preserve more tooth structure:
- professional cleaning for deposits and external stain;
- whitening for responsive natural teeth when suitable;
- orthodontics for position, rotation, crowding and spacing;
- limited edge bonding or repair for a small local defect;
- replacement of a defective filling rather than covering the whole front surface;
- monitoring when the concern is minor and intervention adds more risk than benefit;
- a crown or onlay when a tooth is structurally compromised and a veneer is insufficient.
Alternatives can also be combined. Orthodontics may reduce the amount of restorative change required; whitening may allow fewer teeth to be veneered; gum treatment may create stable tissue before final impressions. “Veneers or nothing” is rarely an adequate consent discussion.
How many teeth should be treated?
The number is not selected from a standard package. The clinician should record how many teeth show in a natural smile, which teeth need a change, how the restorations will transition into untreated teeth and whether whitening can harmonise the remaining natural teeth. Treating every visible tooth can be unnecessarily invasive; treating too few can create an obvious edge in colour or shape.
Photographs with cheek retractors may expose teeth that are not seen in daily speech. A wide posed smile may display more than a relaxed smile. Videos of talking and smiling can help define the visible zone. The goal is not a mathematically identical row but a coherent transition that respects healthy tooth structure.
Ask for a tooth-by-tooth plan showing:
- which teeth receive composite, porcelain, crowns or no restoration;
- which teeth will be whitened and when;
- the planned edge and side additions;
- the expected preparation on each tooth;
- how side teeth will match in colour and brightness;
- what happens if the mock-up shows too much width or length.
Maintenance is part of the after picture
Veneers can chip, crack, wear, stain at margins or debond. Teeth can still develop decay near or under a restoration, and gums can become inflamed or recede. The ADA recommends fluoride toothpaste, daily cleaning between teeth and avoiding habits such as nail biting or chewing hard objects. Individual recommendations may differ.
Composite may need repolishing, edge repair or addition. Porcelain may retain surface gloss and colour well but can still fracture or require replacement. Neither material is permanent. Replacement may involve further tooth treatment, especially after repeated cycles, so the first decision should include a long-term restoration pathway.
The maintenance agreement should specify:
- the review schedule based on personal disease and restoration risk;
- cleaning products and techniques for margins and contacts;
- whether a protective appliance is advised for grinding or sports;
- who handles polishing, repair, rebonding or replacement;
- what is included in an initial adjustment period;
- how urgent problems are handled when the patient lives abroad.
A technically attractive “after” image taken on delivery day says nothing about this plan. Long-term value comes from healthy supporting teeth, maintainable contours and access to review and repair.
Planning veneers away from home
Dental travel adds timing and continuity questions. Porcelain veneers may involve records, tooth preparation, provisional restorations, laboratory or milling steps, try-in, bonding and follow-up. Composite treatment may be completed directly but still needs assessment, consent, bite review and a polishing or adjustment plan. A compressed itinerary should not remove these safeguards.
Before booking, ask who performs the examination, preparation, design, provisional and final bonding. Confirm the restoration material, laboratory or fabrication route, appointment sequence and realistic time for adjustments. Plan what happens if the gums are not healthy, the mock-up is rejected or the bite requires another step.
Take home copies of relevant records: baseline and final photographs, scans or impressions where available, tooth-by-tooth treatment chart, material information, shade, bonding notes, bite or appliance instructions and emergency contact pathway. A local dentist may need these details if a veneer chips, loosens or becomes painful.
Red flags hidden by a beautiful result
Pause when a gallery or consultation relies on any of these patterns:
- the same shade and shape promised to every patient;
- no clinical examination before a deposit or irreversible decision;
- “zero tooth damage” without a tooth-specific preparation record;
- composite or porcelain described as permanently reversible;
- all treatment alternatives dismissed without explanation;
- no disclosure of whitening, gum treatment, orthodontics or crowns in the result;
- different camera angle, exposure or lip position between images;
- no provisional, adjustment, maintenance or repair pathway;
- treatment offered by an unlicensed “veneer technician” rather than a dentist;
- guaranteed shade, lifetime result or exact duplication of another patient’s smile.
The ADA has warned that dental procedures altering teeth, gums or jaws without dentist supervision can cause irreversible harm and that veneer treatment should be provided by licensed dentists. Provider registration and the legal scope of practice should be checked in the relevant country.
A 12-question consultation checklist
- What diagnosis explains each colour, shape, spacing or wear concern?
- Which changes can be achieved by cleaning, whitening or orthodontics instead?
- Are composite, porcelain, crowns or a combination being proposed, and why?
- Which exact teeth will be treated, and which will remain natural?
- How much enamel or existing restoration will be removed from each tooth?
- Can I see a wax-up or reversible mock-up before definitive preparation?
- How will length, speech, lip support and bite be tested?
- What shade, texture and translucency features will avoid an artificial result?
- How will the margins and spaces between teeth remain cleanable?
- What does the quoted price include for provisionals, adjustments, appliance and review?
- Who handles chips, debonding, sensitivity or bite problems after I return home?
- May I consent to clinical records while refusing public promotional use?
The answers should be written into a treatment plan rather than left as a sales conversation. Cost depends on diagnosis, material, tooth count, preparatory treatment, laboratory, location and current clinical conditions; a fixed universal price cannot represent these variables.
Planning with Redent Klinik
Redent Klinik can be approached for individual assessment rather than replication of a gallery smile. Useful first-discussion material includes natural-smile photographs, the main concerns in priority order, previous orthodontic or restorative treatment, sensitivity, grinding history and any existing crowns, fillings or veneers.
The Redent Klinik contact page can be used to ask which records are helpful before a visit and which decisions require examination. Remote images can clarify goals but cannot show decay, enamel thickness, cracks, gum health or functional contacts sufficiently for definitive treatment.
A patient-safe proposal should explain alternatives, tooth-by-tooth preparation, material, provisional stages, number of visits, limitations, aftercare and continuity. A mock-up can help explore proportion and length, but final consent should follow a clinical discussion of biological cost and long-term maintenance.
veneers before and after frequently asked questions
Can veneers before and after photos predict my result?
No. They can demonstrate a clinician’s documented approach or illustrate possible changes, but your enamel, gums, bite, tooth position, colour, restorations and preferences are different. Use images to create questions and a mock-up to test a personal design, not to demand an exact copy.
How can I tell whether the “after” image is final?
Ask for the date and stage. A digital design, removable mock-up, provisional restoration, immediate bonding photograph and settled review are different. A reliable caption states which stage is shown and whether whitening, gum treatment, orthodontics or other restorations contributed.
Do veneers always require enamel removal?
Preparation varies with the starting tooth and intended result. Many porcelain veneer plans involve enamel removal; some additive composite or selected minimal-preparation cases may involve less. “No-prep” should be supported by a tooth-specific record rather than assumed from a brand or package name.
Are composite veneers reversible?
Composite can often be repaired or modified, but complete removal without altering enamel may be difficult, especially when tooth and resin are similar in colour. Ask what preparation is planned, how removal would be controlled and whether “reversible” refers only to a temporary mock-up.
Why do gums sometimes look different after veneers?
Cleaning, resolution of inflammation, tissue retraction, contour changes, gum treatment, camera angle and healing can all affect the gum frame. An immediate photograph may not show settled tissue. Persistent bleeding, swelling, recession or difficulty cleaning requires professional review.
Can veneers make crooked teeth look straight?
They can mask selected shape or position differences but do not move roots. Significant crowding or rotation may require substantial reduction or bulky additions. Orthodontics can be a more conservative option in some cases, alone or before limited restorative treatment.
How many veneers do I need?
There is no standard package number. It depends on which teeth show, which teeth actually need treatment, transition to natural teeth, colour plan and alternatives. A tooth-by-tooth proposal and smile video are more useful than counting the restorations in another person’s photo.
Can I whiten veneers later?
Whitening products lighten responsive natural teeth but do not predictably bleach porcelain or composite restorations in the same way. Plan whitening before final shade selection when appropriate. Later colour mismatch may require polishing, repair, replacement or careful whitening of adjacent natural teeth.
What if a veneer feels high or affects speech?
Contact the treating dentist for assessment. Some adaptation can occur, but persistent high contact, pain, bulk, altered speech or difficulty chewing should not be ignored. Adjustment must preserve material integrity, margins, bite and appearance.
Can a clinic use my before-and-after photos without permission?
Privacy and consent law depends on the jurisdiction, but professional standards generally require informed permission for taking and promotional use of identifiable patient images. Ask how and where images will be used, whether you can withdraw consent and whether refusal affects care.
Final perspective: trace every visible change to a clinical decision
The best veneers before and after review is not impressed by whiteness alone. It identifies colour, edge position, proportion, spacing, symmetry, gum frame, texture and treatment scope, then connects each change to a diagnosis and a named procedure. What is hidden, including enamel preparation, bite, bonding substrate and cleanability, deserves equal weight.
Distinguish a design from a mock-up, a provisional from final porcelain, and an immediate photograph from a settled review. Compare composite, porcelain and conservative alternatives on biological cost, repair, maintenance and continuity. No photograph can guarantee an individual result, but careful records can support clearer consent and safer decisions.
The World Health Organization oral health fact sheet places prevention and treatment of oral disease within lifelong health. Cosmetic restorations should be built on disease control, effective home care and maintainable professional follow-up, not used to conceal untreated problems.
Sources and further reading
- American Dental Association MouthHealthy: Veneers
- American Dental Association: Public Warning About Unlicensed Veneer Services
- American Dental Association: Materials for Indirect Restorations
- General Dental Council: Guidance on Advertising
- General Dental Council: Consent for Before-and-After Images
- General Dental Council: Composite Bonding Insights, April 2026
- World Health Organization: Oral Health Fact Sheet